Ask and answer directly
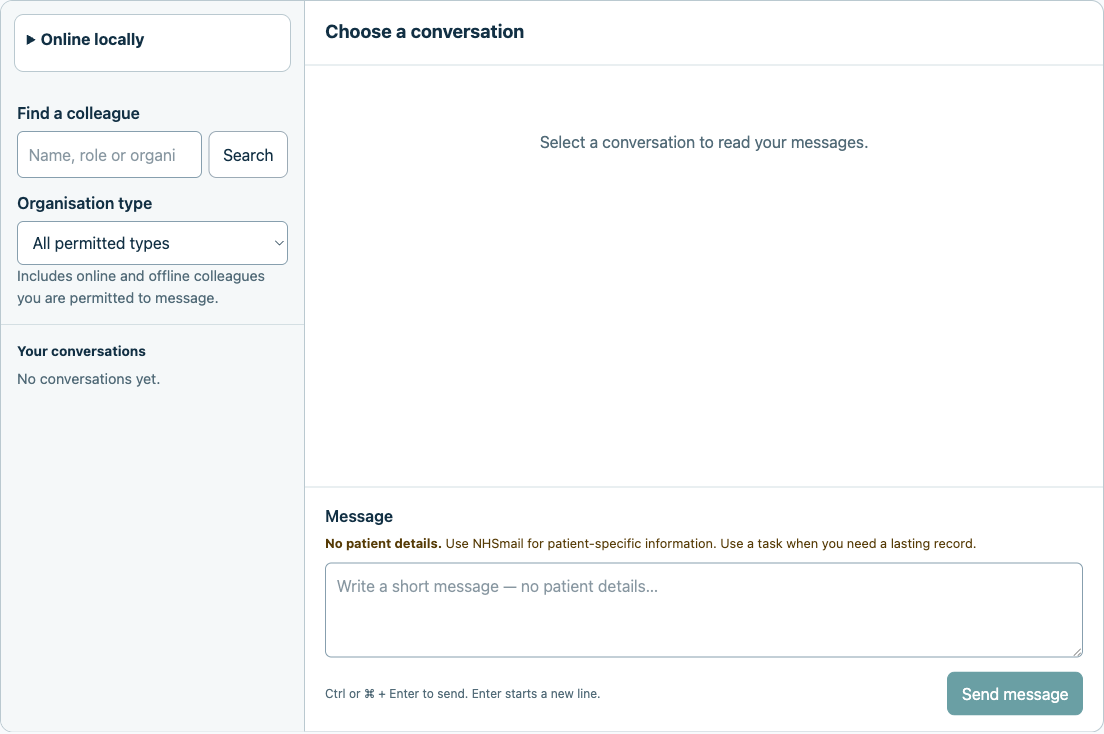
Use instant messages for an exact-medicine question. Chat expires after 48 elapsed hours; a reviewed follow-up task keeps an ongoing action visible. Response times depend on participating teams.
For GP, pharmacy and medicines optimisation teams
Prosper connects GP practices and pharmacies to clarify medicine supply, compare cost opportunities and follow work through to a recorded outcome. ICB teams can review shortage activity and coordinate additional support. Clinical decisions remain with the treating teams.
The local execution gap
Official intelligence and professional judgement remain essential. Local teams still need to see what was checked, who owns the next step and what remains unresolved.
Four software workflows
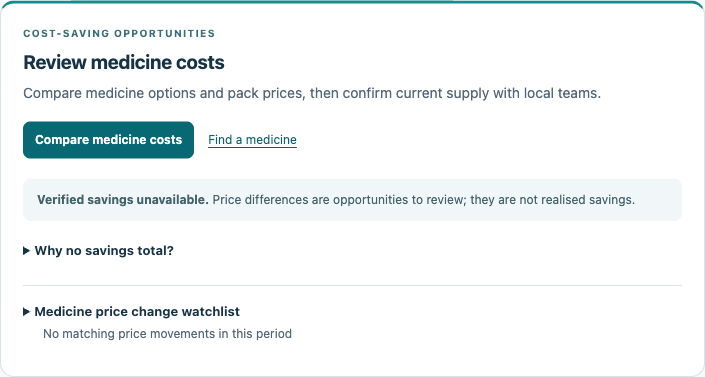
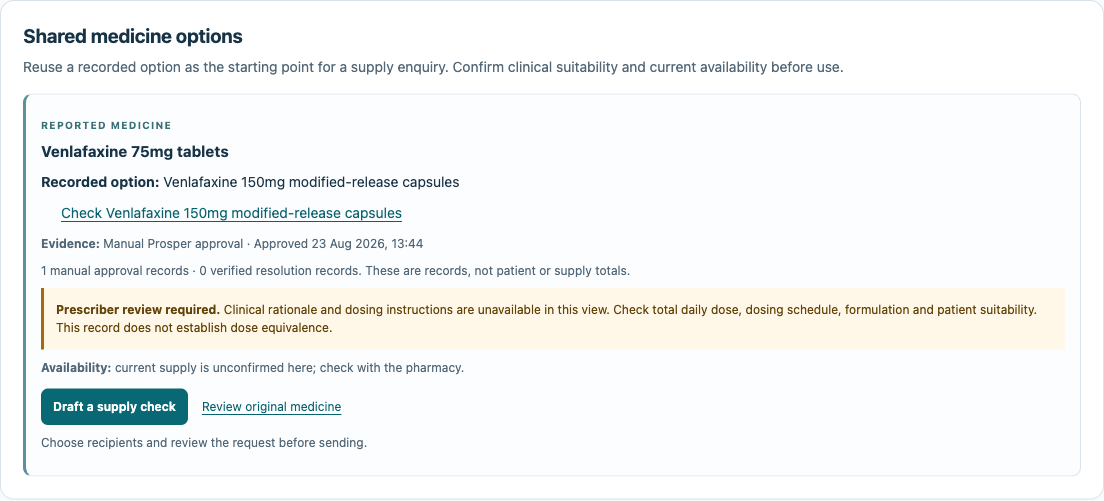
Explore direct messages, enquiries to selected pharmacies, medicine cost comparisons and shared recorded options.
4 product screens rotate automatically. Use the previous and next buttons, the slide buttons, or the left and right arrow keys to change screen. Use pause to stop automatic rotation.
Screenshots from shortage.prosperhealthcare.co.uk, captured on 20 October 2026. They show the live interface and its recorded information; they do not establish measured benefits or verified savings. Select a screenshot to inspect the full capture.
Supply coordination and follow-up
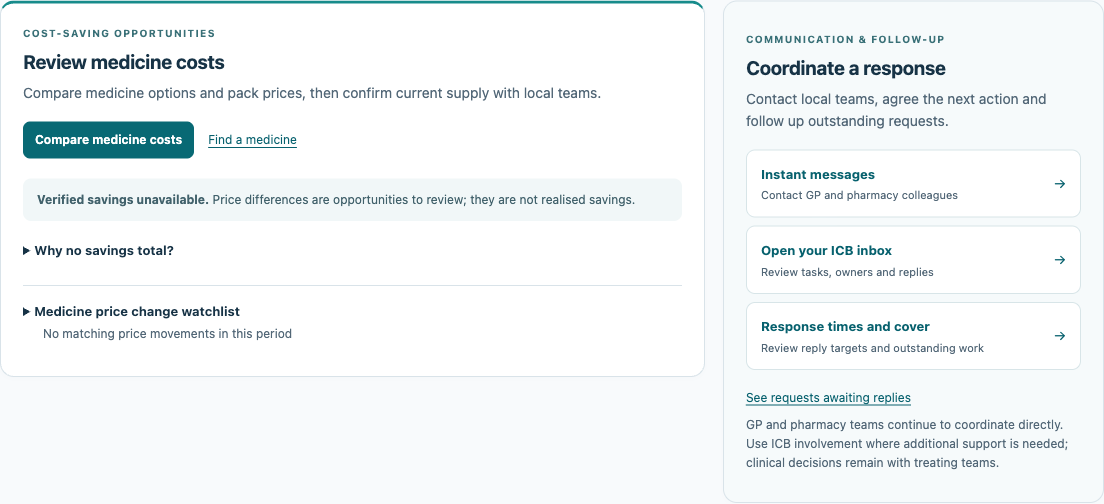
Contact the right team, compare a suitable obtainable option and keep continuing actions in a tracked task.
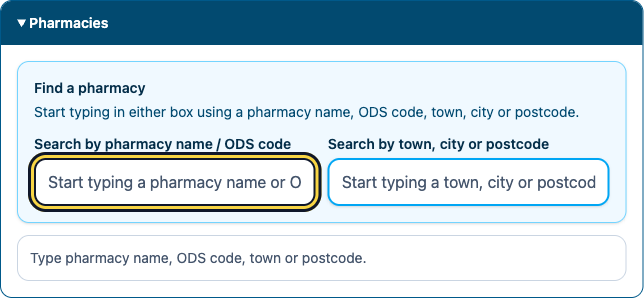
Use instant messages for an exact-medicine question. Chat expires after 48 elapsed hours; a reviewed follow-up task keeps an ongoing action visible. Response times depend on participating teams.
Carry the selected medicine into a task, use an approved template where available and choose permitted recipients. Each task and reply remains separately traceable.
Review comparable product and price information, confirm supply with the pharmacy and record the outcome. Another clinician can use recorded options as the starting point for a fresh check.
One workflow, different views
Practices and pharmacies coordinate routine supply work directly. ICBs review cost opportunities and operational performance, and help where wider coordination is useful.
Reply to supply questions, maintain dated availability and publish service scope, access arrangements and review dates to selected practices.
Check dated medicine information, ask selected pharmacies and discover services. Review clinical suitability and keep the patient plan in the clinical record.
Open cost comparisons, linked shortage reports and your ICB team work. Support participation and evaluate staff effort and outcomes. Provider inboxes remain private; treating teams retain clinical decisions.
Evidence before scale
An evaluation should test whether the workflow improves operational clarity without adding avoidable burden. It should not start with a promise of savings.
Discussion proposal: one willing GP practice and three pharmacies testing agreed shortage workflows. Participants, authority, definitions, dates, support and price must be agreed before starting.
Confirm willing organisations, shortage workflows, monitoring, cover and review criteria.
Record coordination effort on both sides. Finish five elapsed days of follow-up per case before training.
Observe comparable shortage work, including software and reporting effort. Follow each case for five elapsed days; retain unanswered work.
Compare staff effort, repeat contacts, useful answers and unresolved work. Review medicine expenditure separately. Extend collection if coverage is inadequate.
Clear public scope
This overview covers medicine-level coordination, professional cost comparison and recorded operational outcomes. Use established urgent-care routes when a response cannot wait. Patient-specific decisions and records remain in the authorised clinical system.
Review the role views and workflow using synthetic non-patient information.
Subject to local review, agreed scope, governance and authorised access.
Review the exact product, quantity, source date and availability. Treating professionals retain clinical decisions; displayed prices are not verified savings.
Start with workflow fit
Bring a recurring shortage problem. Review four software workflows, discuss the effort and costs, and agree a named lead and dated next decision.
Do not include patient information in booking or registration forms.