Prosper Healthcare Prosper Shortage Manager

Primary and specialist care

Medicine shortages create a chain reaction.

Patients search, pharmacies chase stock, and GP teams absorb rework when local teams do not have one shared view.

Prosper Shortage Manager

Give every medicine-shortage signal a clear owner and next step.

Prosper connects GP practices and pharmacies to clarify medicine supply, compare cost opportunities and follow work through to a recorded outcome. ICB teams can review shortage activity and coordinate additional support. Clinical decisions remain with the treating teams.

Controlled service-evaluation route with no patient data entered at this stage. This public site is not a patient route, prescribing route, clinical advice route, shortage-reporting route or live patient-specific escalation route. Any future patient-data use would require separate governance and is outside the current product scope.
The shortage problem

Shortages are a daily cross-system workflow problem.

The supply issue starts with a medicine, but the workload lands across patients, pharmacies, GP practices, care homes, specialists and local system teams.

1bn+

prescription items

NHS England says primary care dispenses over a billion items a year and handles supply issues daily.

23%

adults affected

Healthwatch found almost one in four adults surveyed could not get needed medicine because the pharmacy ran out.

72%

daily patient impact

Community Pharmacy England reported pharmacy team members seeing patients affected daily.

36

ICB footprints

NHS England lists 36 ICBs in England, so repeated local pressure needs system visibility.

Evidence

Why this is a workflow problem. Official guidance already covers shortage escalation and clinical management. The gap is the local record of what was checked, who owns the next step and whether the same pressure is repeating.

Frustration points

Everyone is asking a different version of the same question.

These are representative frontline phrases, not patient-specific messages. The common theme is uncertainty about supply, ownership and the next step.

Patient

“Where can I get it?”

They do not want to repeat the search.

Pharmacy

“We have checked stock.”

The work is not visible upstream.

GP practice

“What has already been tried?”

The request arrives without context.

Care home

“Will it arrive in time?”

Medicine-round timing creates urgency.

Specialist

“Does this need review?”

High-risk medicines need clean escalation.

Healthcare system

“Where is this repeating?”

Pressure is hard to spot case by case.

Common root cause

No shared shortage record.

Without it, people chase, repeat, reissue and escalate late.

Current response

Guidance supports decisions. Local coordination still needs a shared view.

Teams still need to know what was checked, who owns the next step and whether the shortage remains unresolved.

1

SSPs and guidance

Essential decision support, but not a live view of unresolved local work.

2

Try another pharmacy

Patients repeat the search because previous checks are not shared.

3

Locate stock manually

Pharmacies repeat supplier, branch and practice follow-up.

4

Local reports lag

System pressure becomes visible after frontline workload has accumulated.

Add the missing coordination layer. Prosper works alongside official guidance, professional judgement, stock-control systems and existing clinical records.

See Prosper features

Cross-organisation coordination

One bounded operational view for participating teams.

GP, pharmacy and specialist teams coordinate directly without entering patient data. ICB teams review cost opportunities and shortage activity, support participation and coordinate work that needs wider help. Routine supply enquiries stay between the teams handling them.

Patient focus

One clear next step

ICB teamSupport and review
GP teamDecide
Pharmacy teamSupply
Specialist teamAdvise
  1. 1Share
  2. 2Decide
  3. 3Act
  4. 4Close the loop

Key features

Structured routes through shortage work.

A practical layer for context, ownership and closure.

Connect

Instant messages

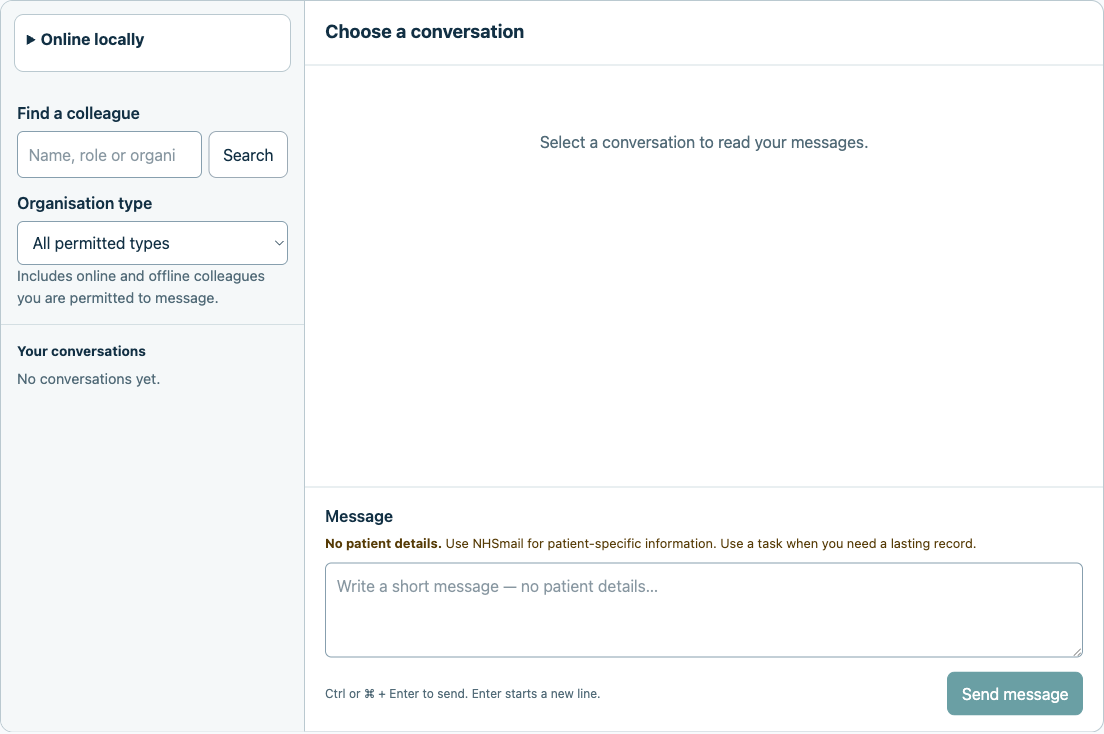
Ask an authorised colleague about the exact medicine and read the reply in the same conversation.

Direct GP–pharmacy contact
Find

See local availability

Time-stamped pharmacy signals with organisation and check time.

Check first
Review

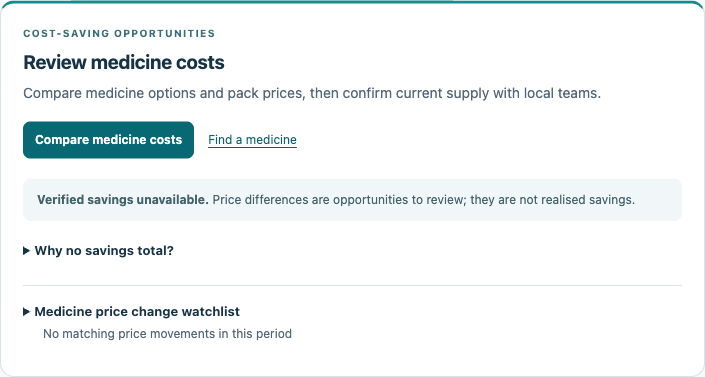
Option and cost context

Compare the exact product, pack quantity and dated price basis. Confirm clinical suitability and supply before acting.

Compare on a consistent basis
Align

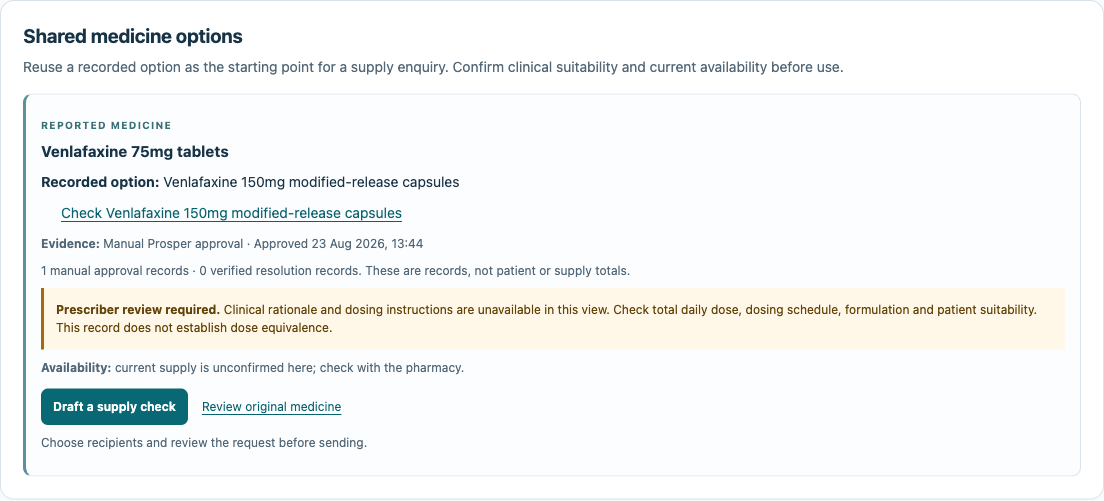
Shared medicine options

Find a recorded option and its evidence status before starting another search. Check the clinical context and current supply each time.

Reuse recorded learning
Act

Enquiries to selected pharmacies

Prepare one medicine enquiry, choose permitted recipients and track each task and reply. Use approved templates where available.

Clear ownership
Detect

ICB costs and performance

Review open reports, closures and cost opportunities. Follow ICB team tasks and response measures within their stated scope.

Review progress and evidence gaps

Keep the next action clear.

Use instant messages for a quick operational question. Chat messages expire after 48 elapsed hours; create a reviewed follow-up task when an action needs a lasting record. Response times depend on participating teams. Use established urgent-care routes when a response cannot wait.

Evaluate contacts needed, active staff minutes and useful answers across both teams. A recorded closure does not prove supply, and a price difference does not prove a saving. Local pharmacy service notices and optional provider returns remain available as additional support.

For ICB teams · For GP practices · For pharmacies · Explore the proposed evaluation

Book a 30-minute workflow discussion.

See three software stories, discuss local priorities and agree whether a small evaluation is useful.